

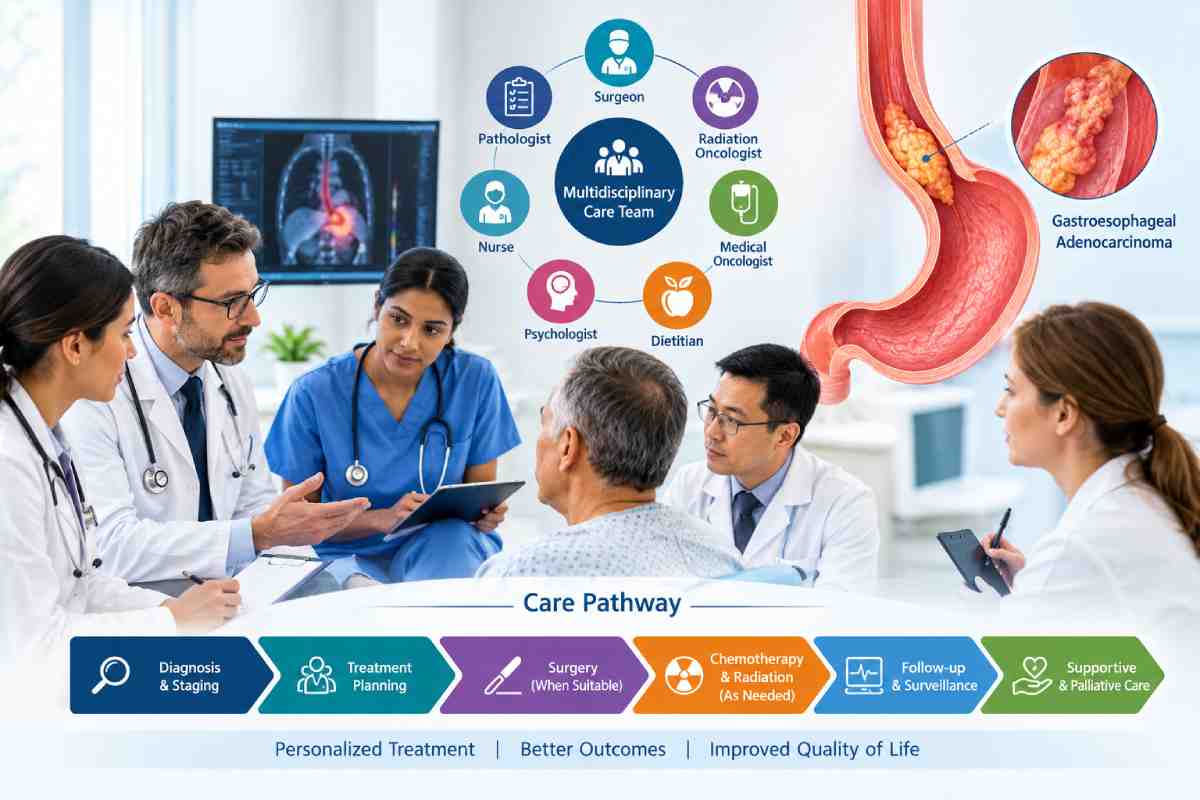
Gastroesophageal adenocarcinoma (GEA) is a heterogeneous disease affecting the stomach and the gastroesophageal junction as well as the lower part of the esophagus. The complex medical management of a patient with GEA requires the joint involvement of diagnostic and therapeutic physicians as well as of nursing staff and representatives from the fields of supportive care. Important criteria when planning the treatment of individual patients are the tumor location and stage, the respective tumor-specific biomarkers, the patients’ general state of health and their degree of tumor-specific therapy tolerance.
A care pathway includes diagnosis and staging of cancer and assessment of the patient’s nutrition and symptom control. Communication with patients and their families and monitoring of patients’ progress through treatment are also important in effective care pathways.
Establishing an Accurate Diagnosis
The first stage of a care pathway is the diagnosis of the tumor and the clarification of the characteristics of the cancer in order to plan the treatment accordingly. The endoscopy and the cutting biopsy are typical for the diagnosis of gastroesophageal adenocarcinoma. The pathological-histological diagnosis of the resected tumor or of the biopsy-material decides about the kind of cancer and enables a consequent therapeutic concept. Imaging studies, in addition to diagnosing cancer, provide information on the extent of the disease and its spread to surrounding structures or to distant sites of the body. Staging cancer is a major consideration in gastroesophageal adenocarcinoma treatment and differs for cancer that is confined to a location, for cancer that has invaded locally and for cancer that has become metastatic.
Additional investigations are also required to obtain sufficient information for the planning of treatment in gastroesophageal cancer. Other investigations are also required to establish the precise diagnosis and to obtain more information on the patient’s symptoms, as well as on his or her general and specific medical history.
The Role of Biomarker Testing
Many tumors express proteins that can be classified into different biomarker types. For example, for eligible patients with gastroesophageal cancer the assessment of human epidermal growth factor receptor 2 (HER2) status can be important because some gastroesophageal cancers are treatable with HER2-targeted therapies.
HER2 status is generally assessed by IHC (immunohistochemistry). For cases where IHC results are equivocal, or in which results indicate low levels of HER2 protein expression, ISH (in situ hybridization) for HER2 gene amplification is commonly performed. Other biomarkers (e.g. PD-L1, dMMR/microsatellite instability (MSI)) are often assessed in clinical circumstances.
The results of the above tests can be inconclusive or need further corroboration from additional tissue samples. In such cases it is sensible to review previous samples for correlational studies. This would ensure that the most appropriate and up-to-date treatment options are considered by the medical team for the patient’s specific tumor type.
Biomarker information needs to be correlated with the clinical stage, patient’s general health and most recent clinical evidence. All information obtained from individual tests does not give a complete picture of the patient’s needs and therefore needs to be clinically interpreted by several people.
Coordinating Multidisciplinary Treatment Planning
In cancer treatment today, the care of patients with cancer is provided by a multidisciplinary team. This team consists of medical oncologists, surgeons, radiation oncologists, radiologists and pathologists. They all discuss individual cases in multidisciplinary meetings or tumor boards. In these meetings the diagnostic findings and staging of the tumor are integrated with the treatment options for the different types of cancer and the corresponding clinical evidence.
The various specialists involved in the diagnostic process of individual cases can also be consulted within multidisciplinary meetings or tumor boards to discuss the various diagnostic and therapeutic options for the respective staging and the corresponding biomarker profile in order to make a joint decision on the optimal diagnostic and/or therapeutic steps for the individual case.
Selection of treatment options depends on a number of factors. For GA cancer in advanced stages of disease, choice of systemic treatment will depend upon the specific characteristics of the cancer and the general health of the patient. All treatment options and their sequencing should be in accordance with current clinical practice guidelines and approved treatment options.
Assessing Overall Health and Supportive Care Needs
As well as a detailed assessment of the patient’s general health, their functional capacity, and their nutritional status, consideration should be made to other co-existing medical conditions. GAEP_A can affect a patient’s ability to eat and swallow thus causing weight loss and dehydration with consequent muscle weakness.
The patient can receive help from a dietitian to overcome nutrition related problems. The patient’s symptoms can be monitored by the patient’s nurse and the patient given advice on how to manage symptoms. Patients can be helped to maintain maximum independence by a physiotherapist and/or rehabilitation team.
All symptoms should be assessed on an on-going basis. Possible intervention(s) should be considered to manage symptoms such as pain, nausea, fatigue and others and supportive care modified as required.
Psychological support to patients with gastroesophageal cancer and their families can also help with anxiety and uncertainty. Patients would benefit from having their caregivers involved as necessary.
Shared Decision-Making and Communication
A patient and their relatives should always be given a complete explanation of a diagnosis and the choices available for the treatment of a disease. Patients should be given the opportunity to make choices based on the doctor’s explanations and the patient’s own preferences about treatment with the possible benefits and complications.
Discussing all options available for the treatment of gastroesophageal adenocarcinoma, its aims and the required monitoring, and the possible impact on daily living of patients with this illness, will enable patients to make an informed choice regarding their treatment goals.
Consistency between specialists is key. They should share up-to-date medical information and ensure that all decisions and actions are recorded and therefore acted upon. A coordinated approach to gastroesophageal adenocarcinoma treatment may facilitate integration of diagnostic findings, treatment planning, and supportive care considerations.
Monitoring and Adapting the Care Pathway
Follow-up is key to managing the effects of gastroesophageal cancer and its treatment. The cancer and its treatment may cause new symptoms to develop. In some cases, patients may find that their cancer treatment becomes too uncomfortable to continue.
However, when a new symptom occurs or a treatment becomes too burdensome for the patient, a reevaluation of the treatment strategy is necessary. This evaluation will be based on the current clinical situation, the state of evidence and the patient’s wishes.
Conclusion
A multi-disciplinary approach is used in managing gastroesophageal adenocarcinoma by combining the diagnostic skills of a variety of healthcare professionals with a variety of treatment options and supportive care services. Accurate staging and use of the correct biomarker tests, along with an assessment of the patient’s overall health and their communication with other healthcare professionals, are crucial in making the best clinical decisions for individual patients.
By providing individualized patient care through ongoing assessment, healthcare professionals within cancer care teams can assist patients in their illness to maintain comfort, preserve function and strive to achieve manageable life while undergoing treatment for their gastroesophageal adenocarcinoma treatment.
